
Below you can read which types of open bite exist, what the causes and possible consequences are, which treatment options there are — from aligners to jaw surgery — and what is known about duration, cost and the risk of relapse. The sources are listed at the bottom of this page.
What is an open bite?
With an open bite, the upper and lower front teeth do not touch when you bring your back teeth together; a vertical gap remains. In a retrospective study of 50 patients, an open bite was defined as a negative overbite of more than 2 mm.
That means the front teeth play no part in biting off food: you bite with the back teeth, not the front teeth. The size of the gap is measured in millimetres, based on the vertical overlap of the incisors.
What types of open bite are there?
Two classifications are used side by side. The first concerns the location in the arch:
- Anterior open bite — the front teeth do not meet, while the back teeth do make contact. This is the most common form.
- Posterior open bite — the back teeth do not meet, while the front teeth do make contact.
The second classification concerns the cause and matters more for treatment:
- Dental open bite — the cause lies in the position of the teeth within otherwise normal jaw anatomy.
- Skeletal open bite — the cause lies in the vertical growth of the jaws. According to a 2021 systematic review, this is often accompanied by a greater lower facial height, a larger gonial angle and a steeper mandibular plane.
This classification is more than a label: it determines whether correction with orthodontics alone is realistic, or whether the position of the jaws themselves plays a part. An open bite is therefore something different from an overbite or a crossbite, which each have their own cause and approach.
What causes an open bite?
An open bite is usually the result of several factors at once. The literature names, among others, the following:
- Thumb sucking or prolonged pacifier use — the habit keeps the front teeth apart and disturbs vertical development
- Tongue thrusting — the tongue pushes forward between the front teeth when swallowing
- Mouth breathing — chronic mouth breathing can change the balance of the facial muscles and promote vertical jaw growth
- Genetic jaw growth patterns — a vertical (hyperdivergent) growth pattern increases the likelihood of a skeletal open bite
- Disorders of the jaw joint — condylar resorption or other joint pathology can cause a progressive open bite in adults
There is a nuance for tongue thrusting: according to a 2021 review, the cause-and-effect relationship between an open bite and atypical swallowing is not yet fully understood.
What are the consequences of an open bite?
Not everyone with an open bite has complaints. This is what research shows:
- Difficulty biting and chewing. In one study, patients with a skeletal open bite (n=33, median age 22) had fewer occlusal contacts than people with a normal occlusion (n=17): on average 13.2 versus 25.4 (p < 0.01). Their jaw movements while chewing were also slower and had a smaller vertical amplitude.
- Speech. Speech complaints are repeatedly mentioned with an open bite; a 2025 systematic review names speaking as one of the domains in which oral health–related quality of life is lower. Whether the open bite is the cause of the speech complaint has not been proven.
- Self-consciousness about your smile. The same review (six cross-sectional studies, mostly a moderate risk of bias) found that an open bite is associated with lower oral health–related quality of life, particularly in the psychological domain and when speaking, eating and smiling. One of the studies found no difference in children.
- Jaw or muscle pain and jaw joint complaints. An association has been described, but no causal relationship. In a population-based study of 4,310 adults, only a bilateral open bite of up to 3 mm was clinically relevantly associated with signs of jaw joint disorders (odds ratio 4.0). That form was rare (0.3%, n=9) and was not confirmed in other population studies.
- Mouth breathing and sleep in children. A 2022 narrative review names an open bite as one of the dento-craniofacial characteristics that can predispose children without a syndrome to sleep-disordered breathing. Mouth breathing is mentioned both as a possible symptom and as a possible predisposing factor.
- Closing the lips and appearance. The introduction of the same study mentions, citing other research, that people with an open bite may have relatively weak chewing-muscle activity, may have difficulty closing the lips and may show a gummy smile. The study itself did not measure this.
In short: for chewing function and experience there are direct measurements; for jaw joint complaints and for sleep and mouth breathing only an association has been described, not a cause. For jaw joint complaints, or when a sleep problem is suspected in a child, a medical assessment is the appropriate route — that is something different from an orthodontic correction in itself.
Open bite in children and in adults
Children. An open bite caused by a sucking habit can improve once the habit stops. A 2023 systematic review (five studies, children aged 4 to 12) found that this often happened: the improvement ranged from 50 to 100%, even in children older than four. The authors themselves rate the certainty of that evidence as very low, and write that it is unclear from what age stopping the habit no longer leads to self-correction. There is therefore no firm age limit to give; an orthodontic assessment can show whether waiting is justified.
Adults. In adults growth is complete and can no longer be influenced; with a correction of the teeth alone (dento-alveolar) the risk of relapse is high. With a pronounced skeletal open bite, other options therefore come into view, such as molar intrusion with skeletal anchorage or jaw surgery (see below). An open bite that develops or gets bigger in adulthood calls for investigation into the cause, especially if there are jaw joint complaints.
How is an open bite treated?
Treatment follows from the cause, the type and the severity of the open bite.
| Treatment | Suited to | Key considerations |
|---|---|---|
| Clear aligners | Mild to moderate dental open bite in adults | Promising, but limited evidence; complex cases often need additional aids |
| Fixed appliances (braces) | Moderate to severe open bites, complex cases | Full bracket control and elastics; one of the options described in the literature |
| Molar intrusion with skeletal anchorage (mini-screws) | Adults in whom the molars need to be intruded | According to a 2021 review, successful correction appears possible; whether the long-term result equals surgery has not been shown |
| Jaw surgery | Pronounced skeletal open bite in adults | Repositioning of the jaw |
| Habit or myofunctional therapy | Open bite with tongue thrusting or atypical swallowing | Most effective combined with orthodontics in children (primary or mixed dentition), according to a 2021 review |
Each of these options has its own place, and they are also combined — for example fixed appliances with elastics, or aligners with mini-screws. An overview of the different types of braces is on Types of braces.
At DenCos in Hoofddorp, specialist orthodontist Dr. Jing Guo uses ClinCheck AI to plan precise open bite corrections. Whether aligners are enough or another approach is needed becomes clear from the 3D analysis made beforehand; see also Invisalign for adults.
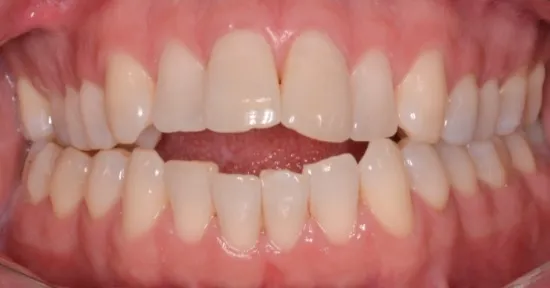
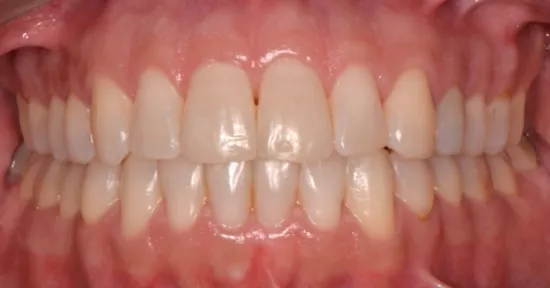
How does Invisalign correct an open bite?
According to a 2024 retrospective study (American Journal of Orthodontics & Dentofacial Orthopedics, n=36 adults), closing an open bite with aligners happens mainly through extrusion and retroclination of the front teeth: in both study groups the open bite was corrected mainly in that way.
In that study, the measured molar intrusion in the group with planned molar intrusion was on average 0.71 mm greater than in the group without — a difference that, after adjustment for confounding variables, was not statistically significant (P = 0.074). Planned molar intrusion therefore showed no demonstrable added value.
A 2025 scoping review (30 studies) also concludes that aligners can achieve measurable extrusion of the front teeth and intrusion of the molars when suitable aids are used, such as attachments and — in more complex cases — elastics or mini-screws. The same review warns that planning software can overestimate the movement that will be achieved, which makes refinement phases necessary.
What is known about the outcome? In a small retrospective study without a control group (n=50), the mean overbite improved from −3.5 mm (SD 1.2) to +1.5 mm (SD 0.8), with 90% of participants reporting better aesthetics and more comfort. Because this is a small, uncontrolled study, it is not evidence of general effectiveness.
The 2025 scoping review names three factors that influence the result with aligners: how consistently the patient wears the aligners, the expertise of the practitioner, and the technological limitations of the system.
Is surgery needed?
That depends on whether the open bite is dental or skeletal. With a skeletal open bite in adults, growth is complete and the problem shifts from the position of the teeth to the position of the jaws.
According to the systematic review by Malara and colleagues (2021), in patients with completed skeletal development jaw surgery is the traditional treatment for an open bite, usually with a Le Fort I osteotomy, with or without a bilateral sagittal split osteotomy of the lower jaw.
There is also the less invasive route: intrusion of the molars with skeletal anchorage (mini-screws). The review found that good results appear achievable this way in patients who are no longer growing, but — because of the varied ways in which outcomes were measured — could not establish whether the long-term results are comparable to those of jaw surgery.
How long does treatment take and what does it cost?
Duration. The only figures we can give come from the small retrospective study above: a mean of 18 months (SD 2.5) and a mean of 24 aligner sets (SD 4.1) in 50 patients. Because the study had no control group, this is not a reliable prediction for your own treatment. A 2025 scoping review points out that refinement phases are often needed with an open bite, because planning software can overestimate the movement that will be achieved.
Cost. Invisalign treatment in the Netherlands typically costs between €2,000 and €4,500, depending on complexity; a full overview is on How much does Invisalign cost?. Orthodontic treatment is in principle not covered by the Dutch basic health insurance: only in cases of a severe (developmental) disorder or abnormality of the mouth may it be reimbursed as special dental care (bijzondere tandheelkundige zorg), regardless of age. Supplementary dental insurance may cover part of the cost — check this with your insurer in advance. The cost of retainers differs by type; you will receive a quote at the consultation.
Can an open bite come back after braces or surgery?
According to a 2021 systematic review, an open bite is among the problems with a high risk of relapse. Two things have emerged from research:
- In the 2024 AJODO study (n=36), 14 patients were reassessed at least one year after treatment; 12 of them (85.7%) had a score of 0 on the Photographic Open Bite Severity Index (POSI), the measure the authors used for stability. The authors themselves speak of a limited sample — it is not a guarantee.
- A 2025 scoping review notes that most studies have little long-term data, so little can yet be said with certainty about the stability of a correction with aligners.
In practice that means:
- Retention — usually a combination of a fixed retainer behind the front teeth and a removable retainer for the night. Many orthodontists advise wearing the removable retainer at night indefinitely to limit relapse in the long term.
- Addressing the cause — with tongue thrusting or another habit, additional therapy makes sense: according to the scoping review, retraining the tongue position with myofunctional therapy can reduce the risk of relapse.
More about retention after the active phase is on Retainers after Invisalign.
Frequently asked questions
Can an open bite in adults be corrected without surgery?
Often, yes, for a mild to moderate dental open bite. A 2021 systematic review found that molar intrusion with skeletal anchorage can correct an open bite in adults, but it could not show that the long-term result is comparable to jaw surgery. For a pronounced skeletal open bite, surgery remains a serious option.
How long does open bite treatment take in adults?
One small retrospective study without a control group (n=50) reported a mean duration of 18 months (SD 2.5) with a mean of 24 aligner sets (SD 4.1). That is not a reliable predictor for your own situation. A 2025 scoping review stresses that refinement phases are often needed, because planning software can overestimate the tooth movement that will be achieved.
What does open bite treatment cost, and is it reimbursed?
Invisalign treatment in the Netherlands typically costs between €2,000 and €4,500, depending on complexity. Orthodontic treatment is in principle not covered by the Dutch basic health insurance: only in cases of a severe (developmental) disorder or abnormality of the mouth may it be reimbursed as special dental care (bijzondere tandheelkundige zorg), regardless of age. Supplementary dental insurance may cover part of the cost — check this with your insurer in advance.
Is Invisalign or fixed braces better for an open bite?
Which of the two works better has not been established. A scoping review of 30 studies (2025) calls clear aligners a promising alternative to fixed appliances in adults, but the evidence consists of case reports and observational studies, and the authors call for high-quality comparative research. Complex cases often need additional aids. The choice depends on your teeth, the cause and the analysis.
Can an open bite come back after braces or jaw surgery?
Yes. In the literature, an open bite is known as a malocclusion with a relatively high risk of relapse. In a retrospective study (n=36), 12 of the 14 patients with at least one year of follow-up no longer had a measurable open bite — a sample too small to treat as a guarantee. Retention and addressing the cause remain decisive.
What are the consequences of leaving an open bite untreated?
A systematic review of six cross-sectional studies (2025) found that an open bite is associated with lower oral health–related quality of life, mainly in the psychological domain and when speaking, eating and smiling. In one study (n=33, median age 22), patients with a skeletal open bite had fewer occlusal contacts and slower jaw movements than people with a normal occlusion. An association with jaw complaints has been described, but not a cause.
Does an open bite go away on its own?
In young children it can, if the open bite came from a sucking habit. A systematic review (2023, five studies) found that the open bite often improved after the habit stopped; the improvement ranged from 50 to 100%, even in children older than four. The certainty of that evidence is very low. The review covered children aged 4 to 12; in adults growth is complete and such an improvement has not been shown.
What is the link between tongue thrusting or thumb sucking and an open bite?
Prolonged thumb sucking, pacifier use and tongue thrusting are named in the literature as factors associated with an open bite. Whether tongue thrusting is the cause or a consequence of an existing open bite has not been clearly shown. A 2021 review concluded that in children with an open bite and atypical swallowing, the combination of orthodontics and myofunctional therapy was the most effective.
Next step
Think you might have an open bite? Register as a new patient at DenCos in Hoofddorp or call 023-792 0463 for a consultation with specialist orthodontist Dr. Jing Guo. The initial iTero 3D scan and cephalometric analysis reveal the exact type and cause of your open bite. Patients from Haarlem, Amsterdam, Amstelveen and Hoofddorp and surroundings are welcome — no referral needed.
Sources
- Finkleman S, Cohanim B, Tai SK, Khosravi R, Huang G. Does planned molar intrusion with aligners assist with closure of anterior open bite? American Journal of Orthodontics & Dentofacial Orthopedics, October 2024;166(4):330-349.e1. Retrospective, n=36 adults. pubmed.ncbi.nlm.nih.gov/38970571
- Karalikkattil TL, Batra N, Vivek CR, et al. Effectiveness of Invisalign Treatment on Open Bite Correction. Journal of Pharmacy & Bioallied Sciences, 2024;16(Suppl 1):S850-S852. Retrospective, n=50. pubmed.ncbi.nlm.nih.gov/38595389
- Olteanu ND, Romanec C, Cernei ER, Karvelas N, Nastri L, Zetu IN. Scoping Review — The Effectiveness of Clear Aligners in the Management of Anterior Open Bite in Adult Patients. Medicina (Kaunas), 2025;61(6):1113. 30 studies. pmc.ncbi.nlm.nih.gov/articles/PMC12195066
- Malara P, Bierbaum S, Malara B. Outcomes and Stability of Anterior Open Bite Treatment with Skeletal Anchorage in Non-Growing Patients and Adults Compared to the Results of Orthognathic Surgery Procedures: A Systematic Review. Journal of Clinical Medicine, 2021;10(23):5682. pubmed.ncbi.nlm.nih.gov/34884384
- Adriano LZ, Derech CD, Massignan C, et al. Anterior open bite self-correction after cessation of non-nutritive sucking habits: a systematic review. European Journal of Orthodontics, 2023;45(3):235-243. pubmed.ncbi.nlm.nih.gov/37080715
- Rodriguez-Huaringa JE, Vargas-Mori GXJ, Arriola-Guillén LE. Influence of anterior open bite on oral health-related quality of life. A systematic review. Journal of Clinical and Experimental Dentistry, 2025;17(1):e87-e95. Six cross-sectional studies. pubmed.ncbi.nlm.nih.gov/39958242
- Kariya C, Kanzaki H, Kumazawa M, et al. Skeletal Anterior Open Bite Attenuates the Chewing-Related Increase in Brain Blood Flow. Dentistry Journal, 2024;12(6):161. OPEN n=33, NORM n=17. pubmed.ncbi.nlm.nih.gov/38920862
- Gesch D, Bernhardt O, Kocher T, et al. Association of malocclusion and functional occlusion with signs of temporomandibular disorders in adults: results of the population-based Study of Health in Pomerania (SHIP). Angle Orthodontist, 2004;74(4):512-520. pubmed.ncbi.nlm.nih.gov/15387030
- Hansen C, Markström A, Sonnesen L. Specific dento-craniofacial characteristics in non-syndromic children can predispose to sleep-disordered breathing. Acta Paediatrica, 2022;111(3):473-477. Narrative review. pubmed.ncbi.nlm.nih.gov/34847264
- Cenzato N, Iannotti L, Maspero C. Open bite and atypical swallowing: orthodontic treatment, speech therapy or both? A literature review. European Journal of Paediatric Dentistry, 2021;22(4):286-290. Children with primary or mixed dentition. pubmed.ncbi.nlm.nih.gov/35034464